Applying for Life Insurance With Past Medical Conditions: Why Resolved Issues Still Count

Life insurers lock in your health class for decades, so underwriters price 20 to 40 years of risk on day one using long-term population data, not just today's checkup. Past high blood pressure, high cholesterol and depression or anxiety still count because of cumulative vascular damage and recurrence rates. Disclose honestly, ask your doctor to mark resolved conditions as resolved in your chart, never stop medication without physician approval, and compare carriers—underwriting guides vary widely.
Why resolved issues still count
Buying life insurance with past medical conditions often feels unfair when you are completely healthy today. You lost weight, fixed your diet, or finished therapy years ago. Your doctor says your high blood pressure, high cholesterol, or anxiety is gone. Yet life insurance underwriters still comb through your old medical records and prescription history.
Insurance ads promise fast, hassle-free approvals, but actual underwriting tells a very different story. Carriers price policies using long-term population statistics rather than your current symptom-free checkup. Understanding how underwriters view resolved diagnoses helps you protect your wallet and secure fair rates.
How life insurance with past medical conditions works behind the scenes
A life insurance policy is a unilateral legal contract. Once an insurer issues your policy, the company locks in your health class for decades. If your blood pressure spikes or depression returns five years later, the insurer cannot raise your rates. Because carriers cannot re-price your policy later, underwriters price 20 to 40 years of risk on day one.
Underwriters do not invent these rules on a whim. Actuarial Standard of Practice (ASOP) No. 12 requires actuaries to group applicants by statistical mortality risk. State laws, including the NAIC Unfair Trade Practices Act (Model #880) and Texas Insurance Code § 541.057, enforce fair pricing. These statutes forbid insurers from charging identical rates to groups with different statistical life expectancies.
Even under ASOP No. 12 Section 3.2.2, actuaries do not need to prove a condition will return in you specifically. They only need credible data showing that people with your medical history experience higher long-term claims as a group.
Cumulative vascular damage: why old blood pressure and cholesterol readings matter
Many consumers treat cardiovascular risk like a light switch. They assume normal lab results today erase five years of high readings. Medical science shows that your arteries keep a permanent scorecard of past stress. Underwriters call this concept cumulative vascular exposure.
A 2019 Journal of the American College of Cardiology study tracked 36,030 adults across six cohorts (Zhang et al., 2019). Researchers measured how early-adult blood pressure and cholesterol affected heart health decades later. Adults under age 40 with LDL cholesterol at or above 100 mg/dL faced a 64% higher coronary heart disease risk. That extra risk remained even when those individuals lowered their cholesterol later in life.
The same JACC study found similar lasting damage from elevated blood pressure in young adults. Systolic blood pressure at or above 130 mmHg before age 40 raised later heart failure risk by 37%. Diastolic pressure at or above 80 mmHg increased heart failure risk by 21%, regardless of normal middle-age readings. Research from the CARDIA study in Hypertension (2020) likewise links blood pressure variability in young adulthood to later atherosclerosis.
A 26-year cohort study in the Chinese Medical Journal (2021) confirmed the danger of cumulative blood pressure load. Participants in the highest 15-year cumulative blood pressure group suffered more than double the cardiovascular events (Hazard Ratio 2.20). Similarly, a 2025 clinical imaging study linked cumulative LDL cholesterol exposure directly to high-risk coronary plaque growth (Odds Ratio 1.411).
Years of elevated pressure or lipids leave microscopic plaque and stiffer arterial walls behind. Underwriters price this lingering vascular wear and tear, even after diet and exercise normalize your lab numbers.
Recurrence risk: why underwriters scrutinize resolved depression and anxiety
Mental health underwriting frustrates applicants who overcame a difficult season years ago. You completed counseling, tapered off medication under a doctor's care, and feel great today. However, actuaries evaluate mood and anxiety disorders using long-term population relapse rates.
Clinical reviews in Frontiers in Psychiatry (2023) and BMC Psychiatry (2025) document high recurrence rates for major depressive disorder. Roughly 50% of people who recover from one depressive episode experience another episode later in life. After two or more depressive episodes, the five-year recurrence rate climbs to nearly 80%.
Reinsurance Group of America (RGA, Reflections Vol. 50, 2020) reports that clinical depression also multiplies physical health risks. Across large insured populations, mood and chronic anxiety disorders correlate with higher cardiovascular disease and metabolic syndrome. They also correlate with disrupted sleep and lower adherence to medical regimens for other illnesses. Because a term policy lasts up to 30 or 40 years, underwriters look for multi-year remission before awarding top rates.
Marketing claims vs. underwriting reality: how carriers check your history
Online insurance commercials promise instant, no-exam approvals at rock-bottom rates in ten minutes. Those commercials leave out the automated data feeds running behind the application screen. Before approving a policy, insurer algorithms scan multiple medical databases to verify your health history.
Pharmacy databases (Milliman IntelliScript and ExamOne LabPiQture): These tools pull five to seven years of prescription fill history within seconds. They show every blood pressure pill, statin, or antidepressant you filled, along with your doctor's specialty.
Medical Information Bureau (MIB): The MIB shares coded alerts from life insurance applications you submitted during the past seven years.
Electronic health records (EHR) and clinical lab feeds: Accelerated underwriting systems pull digital clinic charts, historical lab panels, and diagnostic codes directly from healthcare networks.
Marketing claim: "No medical exam means we only care about your health today." Reality: Algorithms scan five to seven years of pharmacy fills, MIB records, and digital doctor charts.
Marketing claim: "Normal blood pressure or cholesterol gets you our lowest advertised rate." Reality: Carriers check whether medication controls your numbers and average your readings over 12 to 24 months.
Marketing claim: "Past anxiety or situational depression will not affect your life insurance application." Reality: Underwriters verify episode count, medication count, dosage changes, therapy notes, and time since recovery.
Marketing claim: "You can stop taking your pills for a month to pass the insurance physical." Reality: Stopping prescribed medication without physician clearance triggers a non-compliance penalty or an immediate decline.
Costs, risks and the real cost of a lower health class
Applying for coverage without understanding underwriting rules can cost your family thousands of dollars. Every step down the health class ladder increases your premium for the entire policy term.
Life insurers sort healthy and mildly impaired applicants into four primary tiers: Preferred Plus, Preferred, Standard Plus, and Standard. Dropping from Preferred Plus to Preferred typically raises your premium by 15% to 25% per year. Falling from Preferred Plus to Standard often increases your cost by 40% to 70% every year. If an underwriter assigns a substandard "Table Rating," each table adds roughly 25% on top of the Standard rate.
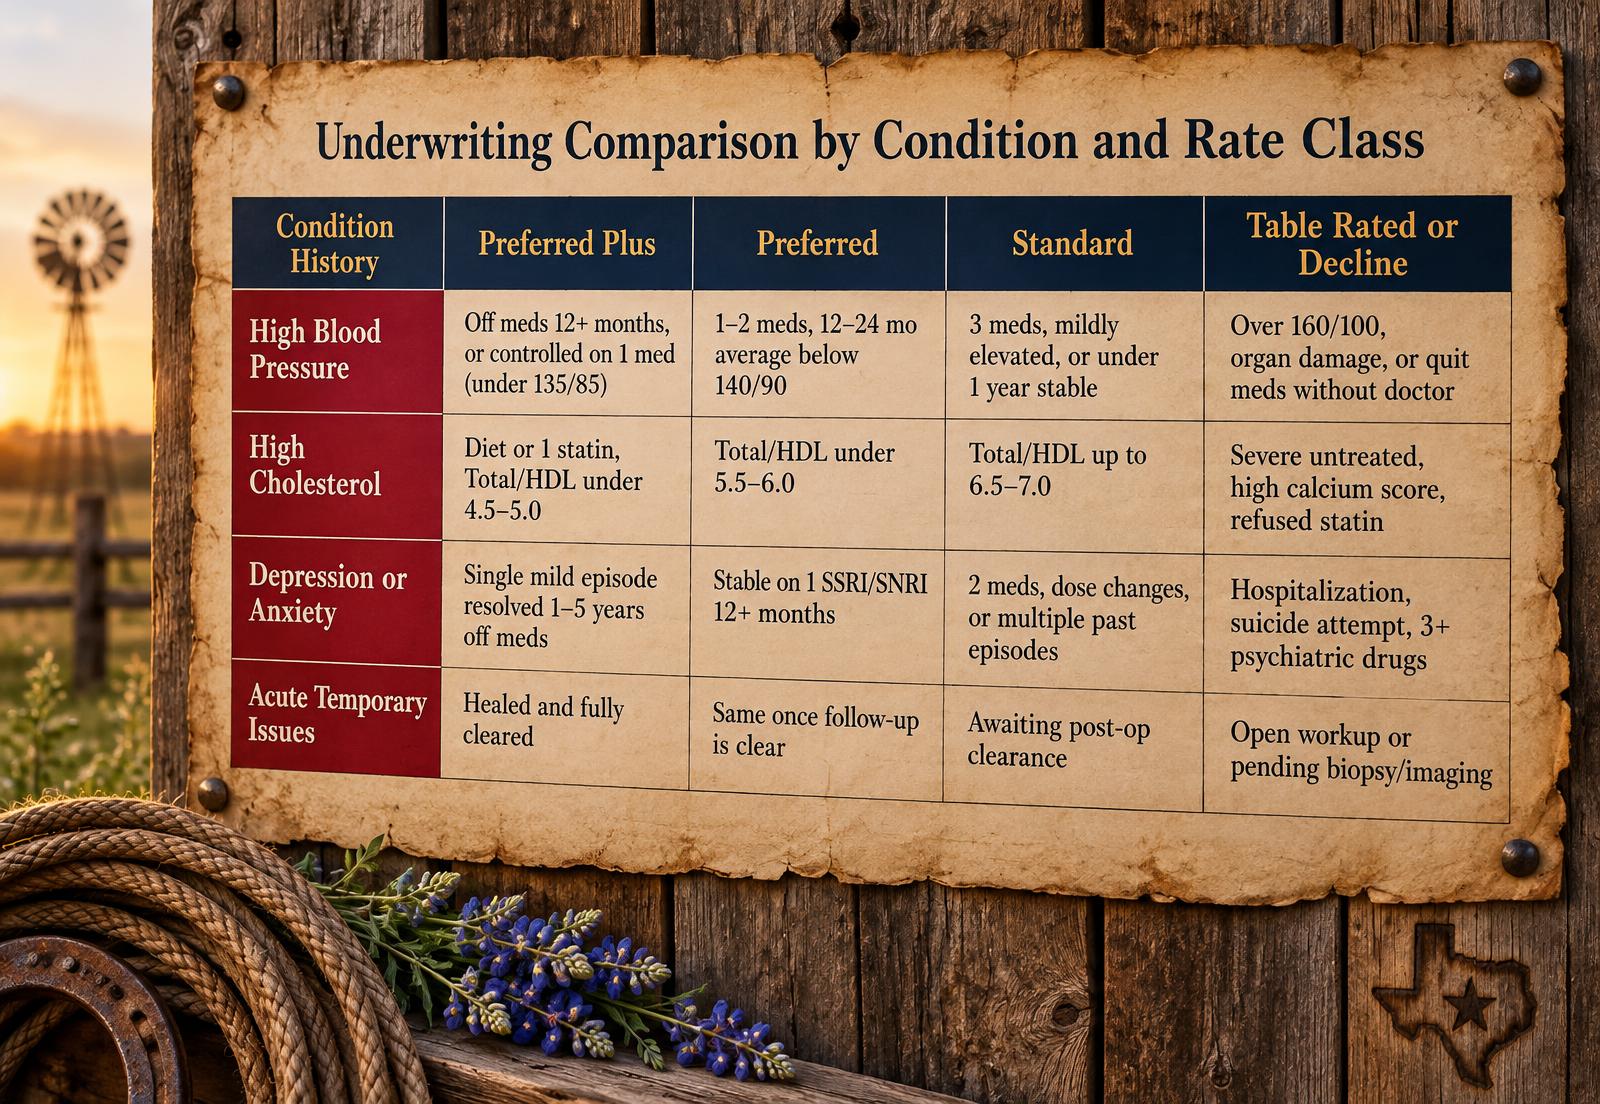
The chart below summarizes how underwriters commonly view each condition by rate class. Guidelines vary by carrier, so treat it as a general guide rather than a promise of any rate.
Four common underwriting failure scenarios
Confusing "controlled" with "resolved": Taking lisinopril, atorvastatin, or sertraline to keep your numbers normal means your condition is treated, not resolved (PLoS One). Marking "no" on an application because your symptoms disappeared while on medication looks like misrepresentation to an underwriter.
Stopping medication without physician clearance: Some applicants quit taking blood pressure pills or antidepressants on their own before applying. When prescription records show past fills but clinic notes show no doctor-approved taper, underwriters flag you for treatment non-adherence.
Unclosed diagnostic loops in electronic charts: Doctors rarely clean up the "Active Problem List" in electronic medical portals. A situational anxiety code from four years ago often sits labeled as "Active" until you ask your doctor to update it.
Ignoring the weight-loss stability window: If you cured your high blood pressure by losing 40 pounds four months ago, underwriters only credit half of that weight loss. Most carriers require 12 to 24 months of maintained weight and drug-free readings to award full credit.
Key limitations and consumer trade-offs
Never lie or omit past diagnoses on a life insurance application. Every policy includes a two-year contestability period. If you die within the first two years and the carrier discovers an undisclosed condition, the insurer can rescind the contract and deny the claim.
You also face a real timing trade-off when a condition recently resolved. Waiting 12 to 24 months after stopping medication might qualify you for Preferred Plus rates. However, waiting leaves your family completely unprotected if an accident or new illness strikes in the meantime. In most cases, locking in a Standard or Preferred policy today and requesting a formal rate reconsideration after 12 to 24 months of documented stability is the safer move.
Real-life scenario: how chart cleanup saved $4,320 on a 20-year term policy
Consider Mark, a 38-year-old nonsmoker applying for a $1,000,000, 20-year term life insurance policy. Three years ago, Mark went through a painful divorce, gained 30 pounds, and developed mild hypertension (142/90 mmHg) and situational insomnia/anxiety. His family doctor prescribed low-dose lisinopril and escitalopram.
Eighteen months ago, Mark lost the 30 pounds through strength training and nutrition. His blood pressure dropped to 116/74 mmHg, and his anxiety resolved. His doctor approved stopping both medications 16 months ago.
When Mark applied online with a rigid insurer, the automated system pulled his five-year pharmacy history. It saw lisinopril and escitalopram fills from two years ago. Worse, his doctor's electronic portal still listed "Essential Hypertension" and "Generalized Anxiety Disorder" under Active Problems. The insurer assumed Mark stopped taking his medications against medical advice and offered him a Standard rate at $92 per month.
Instead of accepting that offer, Mark worked with an independent broker to fix the paper trail. Mark scheduled an annual physical where his doctor recorded a drug-free blood pressure of 118/76 mmHg. The doctor updated both EHR codes to "Resolved" and added a brief chart note confirming physician-directed discontinuation 16 months prior. With that clean documentation and a brief cover letter, a competitive carrier approved Mark for Preferred Plus at $56 per month. That simple chart update saved Mark $36 per month—or $4,320 over the 20-year policy.
This is an illustrative scenario; actual offers depend on each carrier's underwriting and your full history.
Key takeaways for consumers
History predicts cohort risk: Underwriters evaluate past conditions because cumulative arterial damage (Zhang et al., 2019) and condition relapse rates (BMC Psychiatry, 2025) affect 20- to 40-year mortality statistics.
Treated is not resolved: Normal blood pressure, cholesterol, or mood while taking daily medication counts as a controlled condition, though many carriers still offer Preferred or Preferred Plus rates for well-controlled cases.
Never quit medication to pass an exam: Stopping prescribed pills without your doctor's documented approval triggers non-compliance ratings or declines.
Audit your electronic chart before applying: Ask your primary care physician to move resolved conditions off your "Active Problem List" and explicitly note the date you completed treatment.
Shop across multiple carriers: Underwriting manuals vary widely; one insurer may charge Standard rates for treated cholesterol or past anxiety while another awards Preferred Plus.
Conclusion: protect your rate class with facts, not wishful thinking
Life insurance companies do not examine your past health to punish you for old struggles. They do it because a life insurance contract locks the insurer into a multi-decade promise at a fixed price. Vascular exposure from past high blood pressure or cholesterol leaves lasting traces, and mood disorders carry proven statistical relapse risks.
Still, a resolved—or well-controlled—medical history does not doom you to overpriced coverage. By disclosing your history honestly, cleaning up outdated codes in your doctor's chart, and matching your profile to the right carrier's underwriting guide, you can secure reliable protection at a fair price. To review your situation, reach Richard through the contact form.
FAQ
Most life insurance applications ask about diagnoses and treatments from the past five to ten years. Automated pharmacy databases and MIB reports typically display five to seven years of history. However, if a carrier orders an Attending Physician Statement (APS), underwriters can see older medical summaries contained in your doctor's file.
Yes, several major life insurance carriers offer Preferred Plus or Preferred rates to applicants taking one blood pressure medication or a statin. Your readings must stay consistently well-controlled over the past 12 to 24 months, and you cannot have heart or kidney complications.
For a single mild or situational episode of depression or anxiety, many carriers offer Preferred Plus rates 12 to 36 months after your doctor discontinues treatment. Select carriers even allow Preferred or Preferred Plus rates while you take a single low-dose SSRI for mild anxiety or depression, provided your dosage has stayed stable for at least a year.
Pharmacy databases record when a pharmacy fills a prescription, even if you never swallowed a single pill. Ask your doctor to document in your clinical chart why the prescription was written and confirm that you did not need ongoing treatment. Include a short explanation on your application so the underwriter does not assume secret treatment.
Yes, most traditional life insurance carriers allow a formal rate reconsideration after your policy is active for one to two years. You must submit updated doctor records—and sometimes complete a new free paramedical exam—showing sustained drug-free stability and no new health issues.
Sources & further reading
Primary statutory, regulatory, and tax references for the claims in this article. Specific premium quotes and carrier underwriting thresholds are illustrative — confirm with a current quote and the carrier's published guide.
- Zhang et al. (2019) – Cumulative Exposure in Young Adulthood (JACC) — Journal of the American College of Cardiology / PubMed Central
- CARDIA Study (2020) – Blood Pressure Variability & Atherosclerosis — Hypertension / PubMed Central
- Coronary Plaque Progression & Cumulative LDL-C — PubMed Central
- Chinese Multi-provincial Cohort Study (2021) – 15-Year BP Load — Chinese Medical Journal
- Major Depressive Disorder Recurrence (2025 SMARD Protocol) — BMC Psychiatry / PubMed Central
- Major Depressive Disorder Recurrence (2023 Review) — Frontiers in Psychiatry
- Value of Medical Testing in Life Insurance — PLoS One / PubMed Central
- Reflections Vol. 50 (2020) – Depression Underwriting — Reinsurance Group of America
- Actuarial Standard of Practice No. 12 – Risk Classification — Actuarial Standards Board
- Texas Insurance Code § 541.057 – Unfair Discrimination — Texas Legislature
- Unfair Trade Practices Act (Model #880) — National Association of Insurance Commissioners
Want this modeled for your situation?
Twenty-minute call, written recommendation, no hard sell.
Book a free consult